Things to know aboutgastric and duodenal ulcers
Keywords: gastric ulcer, duodenal ulcer, digestive system, H. pylori, Helicobacter pylori
Definition and classification
Peptic ulcer disease is a condition characterized by ulcerative lesions occurring in the mucosal lining of the stomach or the proximal portion of the small intestine (duodenum). An ulcer is defined as a loss of mucosal tissue measuring more than 5 mm in diameter and extending through the muscularis mucosa. The disease is classified into two main types based on anatomical location: gastric ulcers, which occur in the gastric mucosa, and duodenal ulcers, which occur in the mucosa of the duodenum, most commonly in the duodenal bulb – the first segment of the duodenum. Both types share a common pathophysiological mechanism involving an imbalance between aggressive factors, such as hydrochloric acid and pepsin in gastric secretions, and the protective mechanisms of the gastrointestinal mucosa. When the mucosal defense barrier is weakened, tissue injury can extend beyond the epithelial layer and result in the formation of a true ulcer.
Causes and risk factors

Illustration of epigastric pain, a common symptom in patients with peptic ulcer disease.
Causes and risk factors
The two leading causes of peptic ulcer disease are infection with Helicobacter pylori (H. pylori) and the use of nonsteroidal anti-inflammatory drugs (NSAIDs). H. pylori is responsible for approximately 90% of duodenal ulcers and about 60% of gastric ulcers. The bacterium contributes to ulcer formation by disrupting the protective mucosal barrier and increasing gastric acid secretion. NSAIDs cause ulceration by inhibiting the cyclooxygenase (COX) enzyme, which reduces the synthesis of prostaglandins – substances that play a crucial role in protecting the gastric mucosa. Other significant risk factors include cigarette smoking, alcohol consumption, genetic predisposition and family history, advanced age, severe systemic illness associated with physiological stress, and acid-hypersecretion syndromes such as Zollinger–Ellison syndrome caused by gastrin-secreting tumors. Less common causes include malignancies, chronic ischemia due to arterial stenosis, and a history of chemotherapy.
Epidemiology
Epidemiological studies estimate that the prevalence of peptic ulcer disease in Western populations ranges from approximately 5% to 15%. Although the incidence has declined significantly in recent decades due to improved detection and treatment of H. pylori infection, greater awareness of the harmful effects of NSAIDs, and reduced smoking rates among younger individuals, the disease remains common in regions with a high prevalence of H. pylori infection and continues to represent a significant cause of morbidity. Duodenal ulcers are more frequently observed in younger individuals, typically between 20 and 45 years of age, and occur more commonly in men, whereas gastric ulcers tend to develop in older adults.
Pathophysiology
The pathogenesis of peptic ulcer disease is complex and results from disruption of the mucosal protective barrier by gastric acid and pepsin. H. pylori infection plays a critical role by colonizing the gastric mucosa and inducing chronic inflammation, which weakens mucosal defenses and stimulates increased gastric acid secretion through inflammatory responses. In the case of NSAID-induced ulcers, prostaglandins are essential for maintaining mucosal protection, and when NSAIDs inhibit the COX-1 enzyme, prostaglandin synthesis is reduced. This leads to decreased mucus and bicarbonate secretion and reduced mucosal blood flow, making the mucosa more susceptible to acid-mediated injury. In other conditions such as Zollinger-Ellison syndrome, excessive gastric acid secretion is the primary pathogenic factor. In cases associated with vascular disorders or chemotherapy, mucosal injury results from impaired blood supply and weakened mucosal integrity. Ultimately, these processes contribute to the formation of ulcerative lesions.
Clinical manifestations
The clinical presentation of peptic ulcer disease varies widely, with up to 70% of patients remaining asymptomatic. The most common symptom is dyspepsia, typically manifested as epigastric pain or burning discomfort. The characteristics of pain can help differentiate between ulcer types. Duodenal ulcers commonly cause pain during fasting periods, several hours after meals, or at night, and the pain is often relieved by food intake or antacid medications. In contrast, gastric ulcers tend to cause pain that appears or worsens shortly after eating. Associated symptoms may include abdominal bloating, nausea, vomiting, and abdominal distension. Some patients with duodenal ulcers may even gain weight because eating helps relieve pain. Particular attention should be given to alarm symptoms such as gastrointestinal bleeding (hematemesis or melena), anemia, poor appetite, unexplained weight loss, persistent vomiting, or a family history of gastrointestinal malignancy, as these cases require urgent endoscopic evaluation to rule out complications.
Diagnosis
The diagnosis of peptic ulcer disease is based on a combination of clinical manifestations and diagnostic investigations. Upper gastrointestinal endoscopy is considered the gold standard because it allows direct visualization of the ulcer, enabling assessment of its size, location, and severity. The typical endoscopic appearance of a benign ulcer includes a round or oval lesion with smooth, regular margins and a flat base often covered with a yellow-white fibrinous exudate. In cases of gastric ulcers, biopsy during endoscopy is mandatory to exclude gastric cancer, whereas duodenal ulcers usually do not require biopsy and do not necessarily need follow-up endoscopy after treatment unless complications are present. All patients diagnosed with peptic ulcer disease should be tested for H. pylori. This can be done using invasive methods such as the rapid urease test or histological examination of biopsy samples, or non-invasive methods such as the urea breath test or stool antigen test. Computed tomography (CT) scans may detect ulcers or complications such as perforation, while plain radiography may be used as an alternative when endoscopy is not feasible.
Treatment
The main goals of treatment for peptic ulcer disease are to promote ulcer healing, relieve symptoms, eliminate underlying causes, and prevent recurrence. Medical therapy is the primary treatment approach, with proton pump inhibitors (PPIs) such as omeprazole, esomeprazole, and pantoprazole being the first-line medications. These drugs suppress gastric acid secretion and are typically administered for 4 to 8 weeks, or up to 12 weeks in complicated cases. If H. pylori infection is detected, eradication therapy is required. The standard regimen is triple therapy, which consists of a PPI combined with two antibiotics – usually clarithromycin and amoxicillin or metronidazole – for 14 days. Confirmation of successful eradication should be performed after treatment. In addition to pharmacological therapy, eliminating risk factors is essential, including discontinuation of NSAIDs when possible, smoking cessation, and reduction of alcohol intake. Surgical or interventional treatment is reserved for patients who develop complications such as uncontrolled bleeding, perforation, or gastric outlet obstruction, with procedures ranging from endoscopic interventions to laparoscopic or open surgery to repair perforations, control bleeding, or perform partial gastrectomy in rare cases.
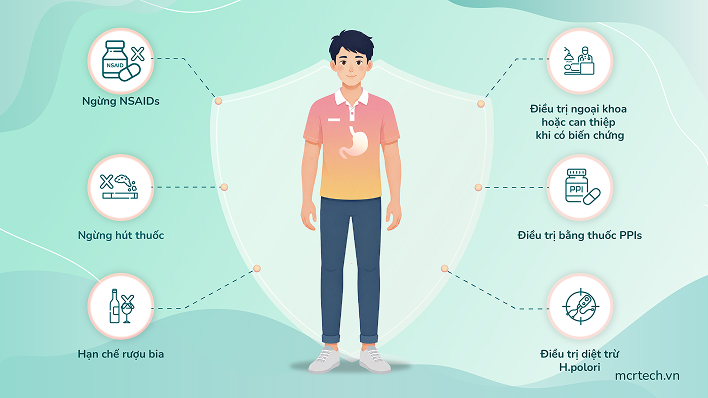
Therapeutic strategies and preventive measures for recurrence of peptic ulcer disease.
Complications
There are three major complications associated with peptic ulcer disease. The most common is upper gastrointestinal bleeding, which occurs when the ulcer erodes into a blood vessel. The severity of bleeding can range from mild oozing to life-threatening hemorrhage, although most cases can be managed endoscopically. Gastrointestinal perforation occurs when the ulcer penetrates the full thickness of the gastrointestinal wall, allowing gastric contents to leak into the abdominal cavity and cause peritonitis. This condition represents a surgical emergency and occurs in approximately 2–10% of complicated cases. Gastric outlet obstruction is the least common complication and results from chronic inflammation and scarring around the pyloric region, leading to narrowing of the gastric outlet and impaired gastric emptying.
Prognosis and prevention of recurrence
The prognosis of peptic ulcer disease is generally favorable when the condition is diagnosed and treated appropriately. Most ulcers heal completely within 4 to 8 weeks of treatment with proton pump inhibitors. Successful eradication of H. pylori and discontinuation of NSAID use significantly reduce the risk of recurrence. However, if risk factors persist – such as continued smoking, prolonged NSAID use without gastric protection, or poor adherence to treatment – the risk of ulcer recurrence and complications remains. Therefore, patient education regarding healthy lifestyle habits, avoidance of risk factors, and adherence to prescribed treatment regimens is essential to achieve long-term disease control and prevent relapse.
References
- Ocasio Quinones, G., & Woolf, A. (2023, April 17). Duodenal Ulcer. In StatPearls [Internet]. StatPearls Publishing. Accessed from https://www.ncbi.nlm.nih.gov/books/NBK557390/
- Barbu, A. M., & Iordache, S. (2023). Gastric and Duodenal Ulcers. In Pocket Guide to Advanced Endoscopy in Gastroenterology (p. 235–239). Springer. https://doi.org/10.1007/978-3-031-42076-4_23